OpenEvidence’s Quiet Raise and Loud Pivot

OpenEvidence just inked a major partnership as it breaks into drug development, and it didn’t even make a fuss about the mega-round it raised to fuel it.

Let’s start with the partnership. OpenEvidence is teaming up with Memorial Sloan Kettering and was generous with the details when explaining the move to Forbes.

  • The collaboration itself was fairly straightforward. MSK is plugging OE into its Epic workflows, and OE is integrating MSK’s OncoKB precision oncology database into its engine to let physicians access the treasure trove of data on genetic variants of different cancers and their treatments.

The fine print was huge. A single sentence bolted onto a paragraph in the middle of the Forbes article revealed that OE quietly raised $250M at a $15B valuation last week. For context:

  • January – $250M at $12B, with a big announcement and press tour for CEO Daniel Nadler.
  • July – The Information reported OE was weighing a $200M raise at $20B.
  • September – $250M at $15B, revealed in a blurb sandwiched between partner coverage.

Not necessarily a down round, but the silence was deafening. Especially considering how much other OE news has been hitting the wire recently:

  • a new family of four AI models featuring Darwin, the first AI in history to score a perfect 100% on the MedQA benchmark.
  • a partnership with Anthropic to give physicians in 100 lower-income countries open access to OE’s clinical decision support.

But wait, there’s more. Nadler told Forbes that OE plans to start developing its own oncology therapies, with the first drug entering clinical trials before year-end and another three candidates on the way next year, starting with rare cancers. 

  • Bit of a head scratcher, but OE isn’t planning to compete with Lilly or Pfizer on 10,000-patient trials. It’s going after “the stuff that they are not doing, and maybe can’t do” because they don’t have OE’s “economies of scale in finding these patients.”

Why go after drug development? Probably the same reason as the funding radio silence – competition is compounding.

  • As OE expands from clinical search into nearby workflows, it’s not only bumping up against Wolters Kluwer and Elsevier, it’s also competing with new heavyweights like Abridge and Doximity.
  • Abridge has giant friends in the pharma space and is only making more, while Doximity just reported a blowout quarter on the back of its solutions that compete directly with OE. 
  • Doximity’s call also snuck in a rumor that an unnamed “major system” is cracking down on shadow AI and banning a product from a direct competitor. Maybe OE, maybe true.

The Takeaway

For all the AI fearmongering that’s been going on recently, it’s nice to see OpenEvidence randomly decide to cure cancer, regardless of the valuation it hit while funding the new quest.

Medallion Gets Its M&A Credentials

Medallion continues building its case to be the go-to platform for provider network management after making its first acquisition with Andros, and it sounds like the shopping spree is just getting started.

Less friction, more healthcare. Providers have to jump through countless operational and compliance hoops before they can start caring for patients, and Medallion specializes in AI-powered hoop jumping.

  • Medallion helps automate away the back-office workflows that delay care – and revenue – such as credentialing, enrollment, and monitoring.
  • The platform not only onboards providers 40x faster, but it also serves as a unified system of record that allows customers to verify credentials, stay in-network, and connect patients to care more efficiently.
  • It also recently unveiled the industry’s first national credentialing clearinghouse, CredAlliance.

Here’s where Andros fits in. Andros has over 13 years of experience as an accredited CVO verifying provider qualifications for commercial payers, health systems, and regional medical groups.

  • It’s built more than 200 provider networks across all 50 states and processes upwards of 300k annual credentialing files.
  • Those customers will now be brought onto the Medallion platform, gaining new AI agents to handle provider outreach and follow-up, real-time status tracking, and human credentialing specialists Medallion embeds alongside its automation.

That makes Medallion the largest credentialing platform out there. It now manages over a million providers across 400+ orgs, but it’s already setting its sights on more M&A.

  • Healthcare is a collection of thousands of billion-dollar markets, and Medallion has the team and funding in place to integrate the pieces that ultimately get providers paid.
  • It’s eyeing companies that are removing the friction to make that happen faster, whether that’s in credentialing, onboarding, compliance, or elsewhere along the way.

The Takeaway

Credentialing is one of the last big administrative functions still running mostly on manual labor, and so far vertical AI plays have barely touched it. Medallion is making the play, and Andros gives it a wider footprint and more momentum to help pull it off.

ACCESS Expands to More Chronic Conditions

Medicare’s experiment in paying tech companies to manage chronic conditions has barely gotten underway, and CMS is already making it bigger.

Advancing Chronic Care with Effective, Scalable Solutions.  ACCESS launched in July to get more companies to lean in on Medicare by rewarding them for using technology to manage diabetes, hypertension, chronic musculoskeletal pain, depression, and anxiety.

  • The model’s core mechanism for accomplishing that is Outcome-Aligned Payments (OAPs), which pays providers more if their patients’ conditions improve.
  • The catch is that these OAPs were “set low” in an effort to encourage innovation that reduces reliance on clinicians, with maximum yearly OAPs ranging from $180 per patient for behavioral health to $420 for cardio-kidney-metabolic conditions.

New tracks are now set to kick off spring 2027. CMS announced that it’s expanding the number of conditions eligible for ACCESS to include substance use disorder, heart failure, COPD, tobacco use, and longer-term support for MSK conditions (a big question mark when the initial model debuted).

  • Put it all together, and about 3 in 4 Medicare beneficiaries will reportedly be eligible for at least one of the tracks.

Who’s participating? Medicare was kind enough to publish the answer in a shiny new directory of providers who can take patients under ACCESS – 39 in total – only a small slice of the 150 companies that were provisionally accepted earlier this year.

  • In: Whoop, Withings, Welldoc, Cadence, and a lengthy roster of smaller players.
  • Out: Omada, Sword, and Hinge, all powerhouses in the chronic condition management space that said the OAP caps wouldn’t support their clinician-heavy models.

Commercial payers are also on board. Although ACCESS is Medicare-only, CMS’s chief AI and technology officer said 17 major health plans covering 165M lives have committed to adopt ACCESS-aligned approaches by 2028, including UnitedHealthcare, Humana, Cigna, and Centene. That’s some real scale if they follow through.

The devil’s in the details. Critics worry ACCESS vendors will fragment care if they don’t loop in primary care, so the model requires PCP outreach and offers small coordination payments. 

  • The expansion also landed one day after comments closed on the 2027 MPFS, which proposes cutting RPM reimbursement because vendor-delivered services fragment care – the exact same thing that ACCESS invites.

The Takeaway

CMS is sticking to its agenda. It wants to pay less for chronic care, and it wants to pay it to whoever can deliver outcomes without a clinician on every call. Whether $420 a year actually gets you better outcomes is now a live experiment with 39 participants.

The Physicians vs AI Debate Goes Another Round

Zeke Emanuel isn’t letting the AMA have the last word in the physicians vs AI debate. A month after his JAMA article with Vinod Khosla predicted autonomous AI will outperform physicians (even physicians using AI) by 2030, he took to STAT to answer AMA CEO John Whyte’s rebuttal point by point.

Whyte’s pushback boiled down to three objections: we lack licensure and liability structures for autonomous AI, doctors are still needed for the “art of medicine,” and most of the supporting evidence comes from simulations rather than real patients.

Emanuel’s counter opens with a history lesson. The piece sets the stage with the surgeons who ignored Joseph Lister’s latest antiseptic data and gave President Garfield a lethal infection by operating on his bullet wound with unwashed hands – “good intentions but ignoring science.” He then works through Whyte’s objections one at a time to help avoid past mistakes:

  • On licensure and liability: it’s true we lack what’s necessary, so build the structures instead of rejecting the technology. Emanuel already published a licensing framework in JAMA, and a liability paper is under review.
  • On the art of medicine: 13 of 15 studies comparing empathy rated AI higher than clinicians, and patient actors felt more at ease with Google’s AMIE than with PCPs (97% vs. 65%).
  • On simulations: the shortage of real-world testing is the fault of doctors, regulators, and laws that block it. The one real-world study of 461 patient visits found physicians produced worse treatment plans than AI even after seeing its recommendations.

Emanuel and Whyte also squared off face-to-screen-to-face. In a spirited debate on the Lifers podcast, Emanuel shared a story about his brother’s two weeks of night sweats that stumped 48 diagnostic tests before Claude nailed a trout-protein reaction from a single query. His brother’s physician reportedly replied, “Does Dr. Claude have malpractice insurance?”

  • The answer to that question sums up the debate perfectly. If autonomous AI is ready for the final say, why hasn’t a single AI company volunteered to own the malpractice liability? State medical boards still hold physicians fully responsible, and no AI vendor has stepped up to shoulder the risk.

The Takeaway

Regardless of where we’re heading, we’ll be in a better spot if we embrace debate. Dr. Zeke and Dr. John just delivered a great one.

Oura Gets Ready to Ring the Bell

It didn’t take long for the Oura IPO rumors to turn into a bonafide S-1, giving us the first real look under the hood of a consumer health company looking to get its AI healthcare platform credentials (and the valuation that comes with them).

Oura’s been busy polishing up the balance sheet. The smart ring OG is on its way to ring the Nasdaq bell ($OURA) with the kind of financials most digital health companies only dream of:

  • $1.2B in revenue for the nine months ended June 30, up 74% YoY.
  • $61M net income on 55% gross margins, up from $1.6M in the same period last year.
  • 5M paid members wearing their ring 23 hours a day. 

Not too shabby. The last bullet is especially impressive, made possible by 94% of activations converting to memberships with a juicy 85% annual retention.

  • Bloomberg reports that Oura is seeking $3B at a $16B+ valuation, up from the $11B notch in its valuation belt that it earned in last October’s $900M Series E.

Those definitely aren’t jewelry numbers. Oura has been positioning itself as an AI-powered health platform sitting on 42B hours of longitudinal biometric data, a dataset that grew 83% in the past nine months alone.

  • It also boasts 1,200+ integration partners that feed clinical data back into the platform. 
  • The member base also looks more like a patient population than the fitness crowd most people would expect: 72% women, more than half reporting at least one chronic condition, and 37% with household incomes under $100k.

Small healthcare beachheads are still beachheads. Oura backs up the health platform by bringing its ring to places like Essence Healthcare’s MA plan (where roughly a third of members opted in), a Cigna benefit collaboration, Lumeris’ care pathways, and Maven Clinic.

  • There’s also the recent Counsel Health partnership that put AI-guided physician consults directly inside the Oura app, and a nice industry ally in partner-turned-investor Dexcom.

Now for the best part of any S-1: the risk factors. Memberships are only 20% of revenue, so this is still a hardware business at its core. 

There’s also a nice pearl about early investors reportedly cashing out $1.09B before the public gets its turn, and a well-timed class action to challenge the accuracy of Oura’s sleep staging numbers.

The Takeaway

Every company has its risk factors, but we’ll always cheer for a big digital health-ish exit. That said, Oura’s S-1 spent a lot of pages telling the SEC what it won’t promise for a company selling “predictive health.”

AI Drives Healthtech’s H1 Ascent

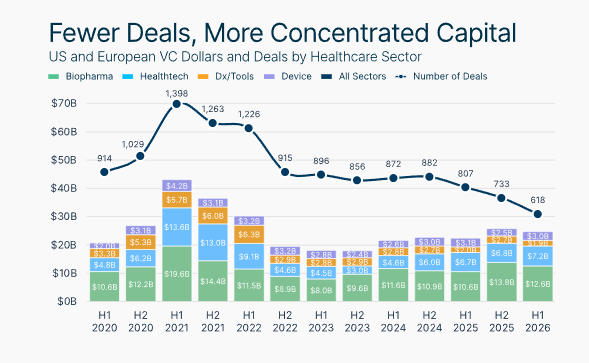
Silicon Valley Bank’s H1 2026 check-in showed bigger investments are going into fewer pockets as the AI power hour continues to motor a red-hot healthtech market. 

The first half of 2026 told a familiar story. Checks are bigger than ever before, but it’s getting harder to cash them.

  • One number is up: Healthtech’s $7.2B H1 set the sector up to outdo its 2025 funding ($13.5B).
  • The other’s down: If H1’s 203 transactions are predictive of the latter part of the year, total deals could fall by nearly a third from 2025, down to a multi-year low.
  • The top six transactions accounted for about 50% of H1 investment.

Funders resurrected “payviders” and skyrocketed late-stage rounds. Last year was rocky for AI-native insurers, but U.S.-focused Devoted and Paris-based Alan got back on track pretty quickly.

  • Devoted reeled in a $366M Series F round, while Alan caught the biggest fish: a $554M Series G. 
  • Median series C+ pre-funding valuations more than doubled since last year, jumping from $3.81B to an almost-otherworldly $8.7B.
  • Series A funding medians also grew 40% from last year, while the middle-of-the-road Series B round dropped 10%. 

Growth happened because AI stayed in the driver’s seat. The top seven Series A funding rounds were brought in exclusively by AI-enabled technologies.

  • SVB pinned healthtech’s success on agentic solutions tackling areas like streamlined revenue cycle management and data infrastructure.
  • Measurement-based care is sticking around. Investors only had time for companies that showed their AI-based solutions provided real-world benefits to clinicians and patients.

Are you in… or are you being acquired?  

  • Exits accounted for a slim $682M so far in 2026, with Kaia Health’s exit being the only one with a return on investments (acquired by Sword for $285M).
  • M&As are carrying their weight, though. The four H1 M&As put 2026 on pace for a five-year high. 


Still, some funds are getting harder to come by. Venture capitalists are tightening their purse strings, as their portion of the investment total is expected to reach a decade low of $10B this year.

And for as good as healthtech is looking, biopharma was the boss (shoutout to our newest sibling, The Bio Wire), bringing in $12.6B. 

The Takeaway 

The future of investments continues to change as VCs grow quiet and fewer companies bring in bigger checks. Nevertheless, H1 2026 was good for healthtech, mainly because AI-powered companies have the numbers to back their impact. 

ChatGPT for Healthcare, Now Available in Epic

The day has finally come. OpenAI just integrated ChatGPT directly into Epic, and the doomsayers were out in full force predicting the instant demise of thousands of startups. 

Here’s what happened (and what didn’t). ChatGPT for Healthcare can now synthesize notes, labs, meds, and specialist documentation to answer questions for clinicians – either by bringing chart context into ChatGPT, or by running ChatGPT in the chart itself.

  • That means that clinicians can easily summarize charts, review labs, and prep for visits without leaving the EHR. Good stuff, not earthshattering.
  • That doesn’t mean that Epic suddenly gave OpenAI access to its 325M patient records, or that ChatGPT can start updating patient records. The connection is “currently” read-only, so nothing’s getting written to the record… yet.

OpenAI didn’t stop there. A new Healthcare Public Data plugin adds structured connectors to nine official sources – including ClinicalTrials.gov, CMS Coverage, DailyMed, and PubMed – for verifying precise information like trial eligibility criteria and coverage policy versions.

  • In early testing on 4,300 responses across 27 clinical use cases, physicians rated 99.1% of the responses as safe. That was apparently good enough for UCSF to sign on as the pilot partner.

The timing talks. Epic spent UGM positioning Ergo as its intelligence layer that sits on top of the chart. Two weeks later, OpenAI began offering its own insights inside that same chart.

  • Agent Factory was also in the UGM spotlight, with 120 AI features slated for wide availability in 2027. Those features definitely aren’t all read-only.
  • Epic still hasn’t said a single word about the OpenAI partnership. 

The peanut gallery talks louder. The thing that most people seem to agree on is that every startup pitching “AI that plugs into your EHR and saves clinicians time” just got steamrolled.

  • Where’s that leave us? “You have to go really clinical.” A model that reads a chart isn’t a workflow-specific product that can act on one. It’s time to specialize and make things happen.

The Takeaway

OpenAI and Epic just officially made chart summaries a commodity. That isn’t the end of thousands of startups, but it will be if they don’t roll up their sleeves.

Get the top digital health stories right in your inbox

Like the website? You'll love the newsletter

Completely free. Every Monday and Thursday.

DHW New Phone Image