Integrating Consumer AI Into Healthcare Pathways

If AI recommends the right care and nobody is around to get it, did it really recommend the right care? A new perspective piece from Topol and friends in Nature Health doesn’t think so.

Four authors, four models. Eric Topol, Yilan Wu, Alvin Liu, and Pearse Keane

sort health AI into quadrants of integration (interface, data, orchestration, workflow) and compare four products by how deep they go:

  • ChatGPT Health – 230M health queries a week and optional record connections, but no orchestration
  • Claude for Healthcare – a consumer arm that connects records and an enterprise arm working the back office (prior auth, claims appeals, coding)
  • Amazon Health AI – links triage to One Medical visits and Amazon Pharmacy fulfillment
  • Ant Group’s Afu – the deepest integration, with booking, physician routing, pharmacy, and insurance payment inside Alipay (140M users, 60% from lower-tier cities)

Models are more than their output. Once a system routes care and moves money, accuracy stops being the only question that matters.

  • Does the patient reach the right care?
  • Does the prescription get filled?
  • What do they pay out of pocket, and where do people drop out?

Those questions need answers. The authors propose that those pathway outcomes (completion, abandonment, cost burden) should become the minimum evidence standard, and each should be reported on individually.

The evidence isn’t keeping up with deployment. None of the four companies has published product-specific performance numbers, and the only independent evaluation the authors could find showed ChatGPT Health under-triaging 52% of gold-standard emergencies.

  • That’s the “infrastructural turn” in a nutshell: systems become hard to bypass before anyone has verified they work.

Epic is the cautionary tale. It became default infrastructure before governance caught up, hospitals adopted its models because they were already integrated, and its sepsis model needed 109 alerts to find one true case.

  • Consumer AI got there in months instead of decades, with no hospital committee standing between the algorithm and the patient.

Closed loops are the sharpest risk. When one company interprets the symptom, routes the referral, fills the prescription, and collects the payment, every step that should be an independent check lives inside the same P&L.

  • Afu is the clearest example, and the authors want routing transparency and conflict-of-interest disclosure treated as infrastructure requirements, not nice-to-haves.

The Takeaway

AI is more than model quality and benchmarks, and it’s great to see more research focusing on the human patient aspects of human patient-facing AI systems.


McKinsey Does the Math on AI-Powered Care

The fine folks over at McKinsey are as bullish as ever on AI, with their latest report estimating that it can already handle over a fifth of U.S. outpatient care.

McKinsey sees AI reshaping healthcare across three vectors. This chart lays them out nicely.

  • Discursive care – reasoning and dialogue but not hands-on treatment (ex. intake, triage). 
  • Personalized pathways – AI trained on individual history to tailor treatment.
  • Autonomous interventions – self explanatory.

The report centers on the first vector. McKinsey analyzed 2024 commercial, Medicare, and Medicaid claims to flag what discursive AI could already own today:

  • 16-22% of all outpatient claims (13-19% of outpatient spending), ~3B claims/yr.
  • Most of that is evaluation visits with no or low-complexity care, 11-15% of claims.
  • The rest is interpretation of diagnostic and imaging results, 5-7%.

Big numbers. McKinsey expects discursive care to fuel the segments where demand goes unmet because of access barriers. Primary care is a prime example, with 92M people living in shortage areas and a 31 day average wait for an appointment.

  • AI stands to make PCPs more efficient decision-makers while improving access for patients, without needing to hire more docs to do it. It also means more diagnostics and specialist referrals.
  • That runs the risk of low-value care cascades, but McKinsey thinks AI would give care teams the confidence to break those cascades and manage more complex conditions in a primary care setting.

Mileage may vary. AI-powered discursive care threatens low-acuity visit volume for fee-for-service orgs, which would need follow-up care, referrals, and procedures to offset the revenue hit.

  • VBC orgs would fare better, using AI to improve their underlying care management economics by catching disease earlier, closing care gaps, and keeping patients engaged.

Who comes out ahead? Payers. With AI becoming the new front door to care, the top of the funnel is shifting from PCPs to whoever can feed the most patient data to the shiniest AI model.

  • McKinsey sees that as payors’ chance to go from financing care to orchestrating it, and says a payor-deployed AI clinician could even become the primary interface patients use to access care.
  • Definitely a hot take, and a potentially brutal hit for fax machine manufacturers. 

The Takeaway

It’s never too surprising when AI consultants say AI can do everything. Then again, that’s turning into a pretty popular opinion.

Heidi Closes Series C and Sets Sights on Clinical Work

Heidi Health just raised $340M at a $900M valuation, which is about $1.4B in their native AUD so they might technically koala-fy as a unicorn.

One round, two vehicles. The funds were split between a $100M Series C led by Blackbird, and $240M in growth financing from General Catalyst’s Customer Value Fund.

  • GC’s Customer Value Fund takes a capped slice of revenue instead of equity so that “companies with good unit economics can push their growth engine without spending their own balance sheet on it.”
  • That not only suggests that GC views Heidi as one of the fastest horses in the ambient scribe race, it also shows that Heidi would rather take on a revenue-share than a company-share. Confidence is key.

The scribe days are over. Heidi was one of the early pioneers of direct-to-clinician AI with its ambient scribe, but it’s since evolved into a complete AI Care Partner for the entire enterprise.

  • This video from CEO Tom Kelly, MD has a great overview of that journey, and explains why Heidi developed its task-specific models that “run circles around the frontier labs” on safety and accuracy.
  • That allowed Heidi to move beyond documentation into aggregating medical evidence at the bedside, routing tasks across the care team, and answering millions of clinical questions every month.

It also helped the platform spread like wildfire. Heidi hit 90% retention before it even had a sales team, and hiring one turned it into one of the most rapidly adopted platforms in healthcare:

  • Supporting 2.8M visits every week across 190 countries and 110 languages. 
  • Scaling ARR from $1M to $50M in two years.
  • Expanding in the U.S. with partners like Beth Israel Lahey, MaineGeneral, and Monash.

What’s on the horizon? Clinical work. Heidi is honing its focus on getting the clerical paperwork off clinicians’ desks, while keeping the medical judgment solely on human shoulders.

  • That means introducing new AI agents to perform the tasks weighing down clinicians outside of visits. “Pre-charting. Chasing diagnostics. Operational friction.”

The Takeaway

Heidi exists “to double the world’s capacity for care.” It’s a big mission, but fair dinkum, and Heidi knows it won’t get there by compiling a list of tasks then handing it back to a clinician to complete. That’s why it raised $340M to build the agents that complete them.

The Physicians vs AI Debate Goes Another Round

Zeke Emanuel isn’t letting the AMA have the last word in the physicians vs AI debate. A month after his JAMA article with Vinod Khosla predicted autonomous AI will outperform physicians (even physicians using AI) by 2030, he took to STAT to answer AMA CEO John Whyte’s rebuttal point by point.

Whyte’s pushback boiled down to three objections: we lack licensure and liability structures for autonomous AI, doctors are still needed for the “art of medicine,” and most of the supporting evidence comes from simulations rather than real patients.

Emanuel’s counter opens with a history lesson. The piece sets the stage with the surgeons who ignored Joseph Lister’s latest antiseptic data and gave President Garfield a lethal infection by operating on his bullet wound with unwashed hands – “good intentions but ignoring science.” He then works through Whyte’s objections one at a time to help avoid past mistakes:

  • On licensure and liability: it’s true we lack what’s necessary, so build the structures instead of rejecting the technology. Emanuel already published a licensing framework in JAMA, and a liability paper is under review.
  • On the art of medicine: 13 of 15 studies comparing empathy rated AI higher than clinicians, and patient actors felt more at ease with Google’s AMIE than with PCPs (97% vs. 65%).
  • On simulations: the shortage of real-world testing is the fault of doctors, regulators, and laws that block it. The one real-world study of 461 patient visits found physicians produced worse treatment plans than AI even after seeing its recommendations.

Emanuel and Whyte also squared off face-to-screen-to-face. In a spirited debate on the Lifers podcast, Emanuel shared a story about his brother’s two weeks of night sweats that stumped 48 diagnostic tests before Claude nailed a trout-protein reaction from a single query. His brother’s physician reportedly replied, “Does Dr. Claude have malpractice insurance?”

  • The answer to that question sums up the debate perfectly. If autonomous AI is ready for the final say, why hasn’t a single AI company volunteered to own the malpractice liability? State medical boards still hold physicians fully responsible, and no AI vendor has stepped up to shoulder the risk.

The Takeaway

Regardless of where we’re heading, we’ll be in a better spot if we embrace debate. Dr. Zeke and Dr. John just delivered a great one.

AI Drives Healthtech’s H1 Ascent

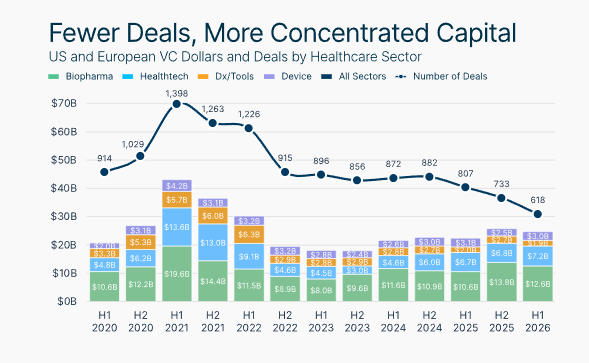
Silicon Valley Bank’s H1 2026 check-in showed bigger investments are going into fewer pockets as the AI power hour continues to motor a red-hot healthtech market. 

The first half of 2026 told a familiar story. Checks are bigger than ever before, but it’s getting harder to cash them.

  • One number is up: Healthtech’s $7.2B H1 set the sector up to outdo its 2025 funding ($13.5B).
  • The other’s down: If H1’s 203 transactions are predictive of the latter part of the year, total deals could fall by nearly a third from 2025, down to a multi-year low.
  • The top six transactions accounted for about 50% of H1 investment.

Funders resurrected “payviders” and skyrocketed late-stage rounds. Last year was rocky for AI-native insurers, but U.S.-focused Devoted and Paris-based Alan got back on track pretty quickly.

  • Devoted reeled in a $366M Series F round, while Alan caught the biggest fish: a $554M Series G. 
  • Median series C+ pre-funding valuations more than doubled since last year, jumping from $3.81B to an almost-otherworldly $8.7B.
  • Series A funding medians also grew 40% from last year, while the middle-of-the-road Series B round dropped 10%. 

Growth happened because AI stayed in the driver’s seat. The top seven Series A funding rounds were brought in exclusively by AI-enabled technologies.

  • SVB pinned healthtech’s success on agentic solutions tackling areas like streamlined revenue cycle management and data infrastructure.
  • Measurement-based care is sticking around. Investors only had time for companies that showed their AI-based solutions provided real-world benefits to clinicians and patients.

Are you in… or are you being acquired?  

  • Exits accounted for a slim $682M so far in 2026, with Kaia Health’s exit being the only one with a return on investments (acquired by Sword for $285M).
  • M&As are carrying their weight, though. The four H1 M&As put 2026 on pace for a five-year high. 


Still, some funds are getting harder to come by. Venture capitalists are tightening their purse strings, as their portion of the investment total is expected to reach a decade low of $10B this year.

And for as good as healthtech is looking, biopharma was the boss (shoutout to our newest sibling, The Bio Wire), bringing in $12.6B. 

The Takeaway 

The future of investments continues to change as VCs grow quiet and fewer companies bring in bigger checks. Nevertheless, H1 2026 was good for healthtech, mainly because AI-powered companies have the numbers to back their impact. 

AMIE Graduates From Chatbot to Video Visits

The moment has arrived. AI is now as good as physicians at conducting real-time video consultations – so long as patients stick to the script.

There’s a new expert in town. It’s Google’s flagship medical AI researcher named the Articulate Medical Intelligence Explorer, but its friends call it AMIE for short. 

AMIE gets its eyes and ears from a three-agent architecture built on Gemini and Project Astra, which splits the job so no single model has to think and respond at the same time:

  • A Talker agent keeps the conversation flowing with low-latency responses.
  • A Planner agent continuously updates the differential diagnosis and clinical goals.
  • A Perception agent watches the live audio-video stream for clinically relevant cues.

Google put AMIE through the wringer. A randomized study pitted AMIE against 10 board-certified PCPs across 100 telehealth scenarios enacted by 15 professional patient actors, with 20 independent physicians grading the encounters.

AMIE matched or beat the PCPs across the board:

  • Overall clinical rubric score: 83% vs. 68%
  • Top-1 diagnostic accuracy: 91% vs. 77%
  • Perception and examination: 74% vs. 47%

The physical exam gap was the eye-opener. AMIE proactively coached patient actors through maneuvers like range-of-motion tests and self-palpation, while the human PCPs mostly fell back on verbal history-taking.

  • Patient actors preferred AMIE for assessing and explaining their conditions, but still preferred humans for rapport, with interviews describing AMIE as having awkward pauses and odd conversational cadence.

Here’s the disclaimer. These were patient actors following scripts, not real patients. The physicians had to keep their cameras off, and AMIE still whiffed on subtle signals like tremors, nystagmus, and affect – the exact cues where perception matters most.

  • That’s not exactly real-world validation, but that’s already underway through a feasibility study with Beth Israel Deaconess and a nationwide study with Included Health.

The Takeaway

When AMIE first prompted predictions that patients would soon see an “AI doctor” before a human one, the missing physical exam was the go-to rebuttal. That gap just got noticeably smaller, and it doesn’t feel like we’ll be able to write too many more of these before it disappears completely.

AI Will Bend the Cost Curve, for Better or Worse

A new paper in NEJM Catalyst makes the case that AI might finally bend the cost curve in healthcare, just not in the direction patients were hoping for.

“Show me the incentives and I’ll show you the outcomes.” National health expenditures jumped 60% to nearly $5T per year in the last decade, and widely cited estimates from McKinsey suggest AI could shave about $360B off the annual total. 

  • Venrock’s Bob Kocher and Brian Zhao teamed up with USC’s Erin Duffy to explore the areas where those savings will allegedly materialize, and they found the same overarching problem with all of them.

You get what you pay for, and fee-for-service pays for volume. No matter where they looked for potential savings, the authors believe AI is even more likely to have the opposite impact.

  • Drug Development – Faster AI-driven discovery means more new drugs and more eligible patients, but a healthier population doesn’t happen overnight. The net effect for the foreseeable future is more pharma spending, not less.
  • AI Scribes – Under FFS, freeing up physician capacity is a direct path to more visits, which is a hop and a skip away from more fees, tests, referrals, and prescriptions.
  • DTC “AI Doctors” – Could be deflationary if they replace pricier human encounters, or inflationary if every chat ends in an escalation and a testing cascade. Early evidence points to cascades.
  • RPM and CCM – AI dramatically cut the cost of delivering remote care by reducing the clinician time needed to analyze the data, but blanket deployment means more billable monitoring and more incidental interventions (see: United Healthcare’s now-paused move to narrow RPM coverage to two conditions).
  • Admin Automation – The AI-generated savings are real, but in consolidated hospital and insurance markets, that translates to higher margins, not lower prices.

Flip the model, flip the outcome. Every one of those buckets cuts the other way under value-based care arrangements, where the AI force multiplier is more likely to get pointed at complex patients and preventive care rather than volume and more volume.

  • At-risk providers are already using AI to expand access, improve screening, and deliver better treatment. The AI upside is there, it’s just not showing up in the places most people are looking.
  • The authors’ most direct policy fix is simple: more value-based care, and more outcomes-based reimbursement efforts like CMS’s new ACCESS model.

The Takeaway

While AI holds enormous potential to improve healthcare, this paper highlights exactly why it takes more than new tech to bend the cost curve. It also takes the right reimbursement models wrapped around it.

2026 Healthcare Forecast Cloudy, But AI Rays Could Poke Through

Venrock’s 10th annual survey of healthcare insiders reveals they’re a pessimistic bunch lately, harboring cynicism about recent policy developments and the future of health tech IPOs, though views on AI were more of a mixed bag. Let’s break down the results. 

But first, a bit about the survey. More than 200 leaders from all corners of healthcare shared their thoughts with Venrock. Some areas were better represented than others.

  • Respondents skewed toward the private sector (28%), investing (20%), life sciences or pharma (16%), professional services (8%), and academia (7%). 

Venrock loaded up the questionnaire with AI inquiries. Big picture: Insiders are becoming more comfortable with the tech, but remain mindful of its downsides. 

  • Trust in AI grew for 73% and fell for 2% (unclear who hurt them). 
  • Just 9% view AI as the most overrated trend in healthcare.
  • HIPAA breaches (24%), harmful hallucinations (19%), and overspending on healthcare-specific platforms (28%) ranked highest among possible AI pitfalls. 
  • Most expect AI to create an costly arms race between payers and providers (63%) as each side rolls out bots specifically designed to argue with other bots.

Here’s another fun one: M&A targets. There’s no consensus on who will get snapped up next, but the industry seems confident it will be a big name in AI-powered services. 

  • OpenEvidence (21%), Komodo Health (18%), Abridge (14%), and Sword Health (11%) were the top answers out of 10 companies, but only after none of the above (46%).

So the hottest firms are going public? Nope — that’s one thing people can agree on. 

  • Only 3% think health tech IPOs will be back in style this year, with the rest split roughly down the middle between 2027 and 2028 or beyond. 
  • For those keeping score, 42% of last year’s respondents predicted a health tech firm would go public in the first half of 2026. Tumbleweeds…

In fairness, it’s hard to predict the future, especially with $1.15T in Medicaid cuts looming over everyone’s heads. 

  • Will they harm rural hospitals? Empty state coffers? Ruin MCOs? Strain blue-state safety net hospitals? Most checked all of the above (65%). 

The Takeaway

Some of the smartest folks in healthcare think we’re heading toward a world of payer-provider bot wars, sluggish health tech IPOs, and brutal fallout from Medicaid cuts. Here’s to hoping Venrock’s survey missed the mark. 

IntelePeer Sister Company Aqurio Enters the AI Agent Fray

Telecommunications company IntelePeer thinks it’s in the right place at the right time to capitalize on rising interest in agentic healthcare AI with the launch of sister company Aqurio. 

IntelePeer cut its teeth during the voice over internet protocol boom of the 2000s, eventually moving toward cloud-based communications services and now AI. 

  • As AI took up more of its focus, IntelePeer decided it was time for a new organization, leading to the creation of Aqurio. 

So what does IntelePeer know about healthcare? Quite a bit, since many of its automated customer service tools are used by providers and health plans. 

  • Through this experience, IntelePeer became keenly aware of the industry’s operational pain points, like billing backlogs and call center wait times. 

But why launch Aqurio now? IntelePeer was convinced by recent advancements in AI. 

  • Specifically, AI can now tackle end-to-end tasks in regulated environments, many of which once took large teams and lots of resources to coordinate. 
  • AI has also become cheaper, with inference costs falling over 95% since 2022. 
  • Wait any longer, and another firm might solve the problems Aqurio is after. 

Aqurio is rolling with three main products, but one platform. By keeping agents unified, the company aims to stop patients and revenue from falling through the cracks. 

  • For administrative tasks, SmartAgent answers calls, texts, and chat messages to support things like scheduling, insurance verification, and billing inquiries.
  • When it comes to outreach, SmartEngage sends collections and patient recall messages on the provider’s behalf. 
  • On the data front, SmartAnalytics combs customer service interactions for insight into KPIs, ROI, human agent performance, and behavior of the other two agents. 
  • As for clinical follow-up, SmartCare handles visit summaries, post-surgical assessment, and symptom flagging.

The agentic AI market may be crowded, with no shortage of well-funded companies, but Aqurio could hit the ground running by leveraging IntelePeer’s foundation. 

  • IntelePeer has logged more than 1B customer interactions. 
  • Aqurio’s platform has HIPAA, HITRUST, SOC 2 Type II, and other certifications out of the gate. 

The Takeaway

With the creation of Aqurio, IntelePeer is aggressively pushing into agentic healthcare AI without sacrificing its core telecommunications business. Time will tell if Aqurio can muscle out the competition, but IntelePeer’s more than 20-year history gives its sister company a massive leg up over three-guys-in-a-garage startups.

New Model Predicts 900 Diseases From Real Records

Last week brought a potentially significant step forward for early diagnosis in the form of a new AI model that can predict a patient’s next diagnosis across nearly 900 diseases using just real-world medical records.

Meet DT-Transformer. Researchers at Harvard, Brigham and Women’s, and the Broad Institute unveiled the GPT-style foundation model in a new arXiv preprint.

  • DT-Transformer reads a patient’s medical history as a sequence and predicts which disease will show up next, and when it might come knocking.

The real headline is the training set. DT-Transformer was trained on 57.1M structured EHR entries from 1.7M patients across MGB’s 11 hospitals and 200 clinics (2000 to 2024) – the messy reality of U.S. clinical care rather than a polished research data set.

The numbers were impressive. A few standouts:

  • DT-Transformer achieved a median AUC of 0.871 across 896 disease categories, with AUC over 0.5 for every condition.
  • The model crushed an age- and sex-based baseline by +0.214 AUC (0.871 vs. 0.657), beating it on 96% of diseases.
  • All of that was accomplished with a featherweight 2.2M parameter model that’s small enough to run just about anywhere (by comparison, Claude Fable 5 has about 6 trillion parameters).

The real test told a humbler story. When the team ran a true prospective test forecasting new diagnoses DT-Transformer had never seen, median AUC slipped to 0.713.

  • That still beats the baseline on 80% of diseases, but that gap between the retrospective flex and the prospective reality is fairly significant.  
  • A 0.871 headline number and a 0.713 crystal ball aren’t the same product, and the second one is the one that patients would actually have to deal with.

One other highlight worth mentioning: including every repeated diagnosis worsened model performance, “drowning out the signal” rather than improving predictions – another reminder that more data isn’t always better. Better data is.

The Takeaway

Population-scale risk forecasting that runs on a model smaller than most phone apps is a real milestone, and training on routine records instead of a spotless biobank is exactly the kind of thing that could get models like DT-Transformer in front of actual patients – assuming the data holds up to peer-review.

Get the top digital health stories right in your inbox